


What is the Mallampati classification and what is it used for?
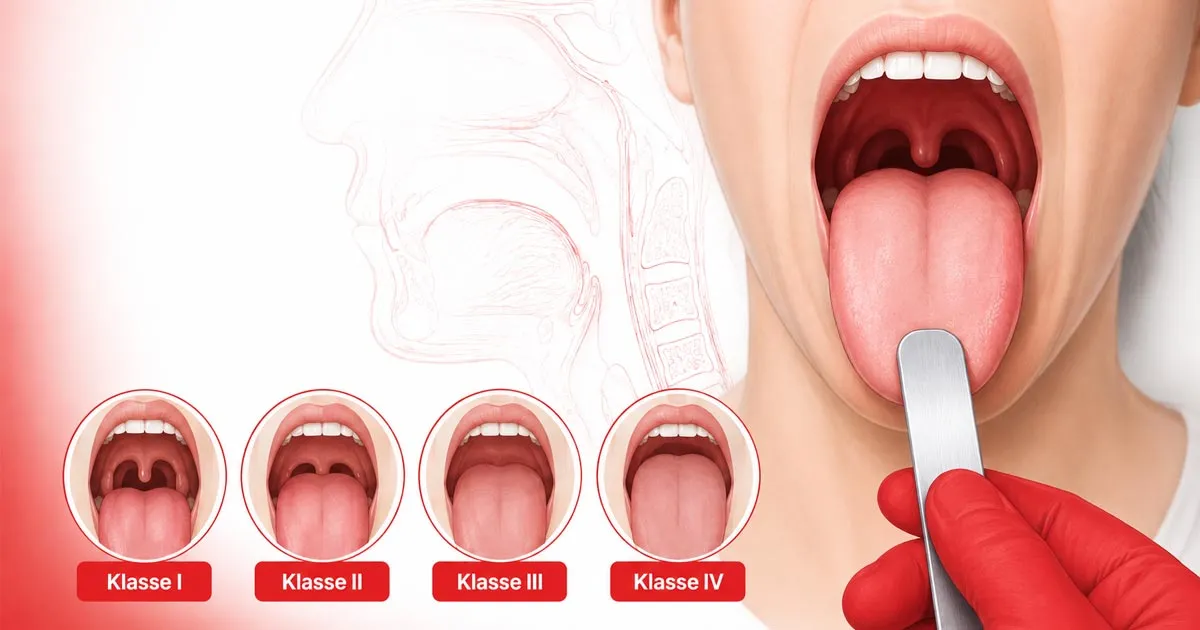
The Mallampati classification (in the form commonly used today, as modified by Samsoon and Young) uses the visibility of the soft palate, uvula and faucial pillars with the mouth open to estimate how good access to the larynx will be at subsequent laryngoscopy. It is one of several predictors of difficult mask ventilation or intubation and is used in the daily pre-anaesthesia assessment.
The four classes are distinguished as follows:
- Class I — soft palate, uvula and both lateral faucial pillars fully visible.
- Class II — lateral faucial pillars and tip of the uvula no longer visible.
- Class III — only the soft and hard palate visible.
- Class IV — only the hard palate visible.
The S1 guideline “Airway Management” of the German Society of Anaesthesiology and Intensive Care Medicine (DGAI) points out that the Mallampati classification alone has limited predictive value and becomes more reliable in combination with the Patil thyromental distance (reference value below 6–7 cm). The guideline also names known weaknesses in practical application — including when used by experienced anaesthesia staff.
Why can the Mallampati classification not be collected through a digital medical history?
The Mallampati classification requires direct visual inspection by a trained person — head position, mouth opening, tongue protrusion and lighting all influence the result, and classification varies even among experienced examiners. A selfie or a description by the patient cannot reproduce these examination conditions.
The DGAI guideline also explicitly places the collection of anatomical and physiological signs of difficult mask ventilation or intubation within the pre-anaesthesia evaluation — that is, the clinical examination by the physician, not the patient’s medical history. In addition to the Mallampati classification, this includes mouth opening, dental status, mandibular protrusion and cervical spine mobility, among others.
In concrete terms, this means: medudoc digitalises the medical history — the history that patients can report themselves (previous problems with anaesthesia, anaesthesia card, known intubation difficulties, a diagnosis of sleep apnoea). The physical examination of the airway remains a medical act that can only take place during personal contact.
What does the process look like with medudoc — from the medical history at home to the airway check in the hospital?
The digital preoperative workflow makes a structured distinction between information that patients can provide and examination findings that physicians must collect; both are brought together in the same structured record.
- At home, by patients: The adaptive digital medical history records pre-existing conditions, previous experience with anaesthesia, known airway problems, signs of sleep apnoea and medication. Follow-up questions adapt dynamically to the answers.
- In advance, via video: Patients watch the personalised patient education video on the planned anaesthetic technique — at their own pace and with the option of rewatching sections on alternative techniques.
- In the HCP Dashboard, by medical staff: The structured medical history data is available in prepared form before the appointment, including completeness status and configurable alerts.
- At admission, by the physician: The examination findings are documented in structured form in the “Airway & Anatomy” module — including Mallampati classification, mouth opening, thyromental distance, cervical spine mobility and dental status. This is an existing product feature of the medudoc platform (as of May 2026).
- By the intubating physician: Immediately before induction of anaesthesia, the intubating physician performs their own airway assessment — in line with the guideline and independently of all previous steps.
| Before admission (digital, by patients) | At admission (in the hospital, by the physician) |
|---|---|
| History of previous anaesthesia and airway problems | Mallampati classification (Class I–IV) |
| Signs of sleep apnoea, dentures, previous surgery in the head and neck region | Mouth opening (interincisor distance), thyromental distance |
| Patient education on anaesthetic techniques and alternatives via video-assisted patient education | Cervical spine mobility (extension/flexion) |
| Structured handover of the information to the HCP Dashboard | Dental status, risk factors for difficult mask ventilation |
| — | Repeat airway assessment immediately before induction of anaesthesia (mandatory, in line with the guideline) |
Which legal provisions govern medical history, airway assessment and patient education in Germany and Austria?
In Germany, taking the medical history is part of the obligations arising from the treatment contract, and the duty to inform is codified in the Patients’ Rights Act (Patientenrechtegesetz). Austria has no nationwide codification in the form of a patients’ rights act; the decisive sources are the Physicians Act (Ärztegesetz), general tort law and specialist guidelines recognised as federal quality guidelines.
Germany
- Section 630a of the German Civil Code (BGB) governs the treatment contract and thus the obligation to take a careful medical history as the basis of any treatment.
- § 630e BGB governs the duty to inform: patient information must be comprehensible, timely and individual. Subsection 2 no. 1 explicitly requires an oral discussion between physician and patient — digital tools can prepare this discussion, but cannot replace it.
- The DGAI S1 guideline “Airway Management” is not a law but a specialist expert consensus (AWMF classification S1). It describes the recognised state of medical science and is therefore relevant to the question of which standard of care is applied in liability cases.
Austria
- Section 51 of the Physicians Act 1998 (Ärztegesetz) governs the duty to document and includes the medical history and the content of the consent discussion; standardised patient information materials are permitted but must be adapted to the individual patient.
- Preoperative evaluation follows the ÖGARI source guideline “Preoperative Patient Evaluation”, which the Federal Health Commission has recognised as a federal quality guideline (BQLL).
- Specifically on the difficult airway, the ÖGARI information sheet “The Difficult Airway” is available.
German and Austrian law agree on one central point: standardised or digital patient education content is permitted and even explicitly provided for — but it must be tailored to the individual patient, and the face-to-face discussion remains a mandatory part of the process. You will also find a country-specific overview for Austrian hospitals in our article on informed consent in Austria, and further background for the German market in the legal basis of patient education.
How does patient education remain individual when a patient education video is used?
Whether patient education is individual does not depend on whether a video or a discussion is used, but on whether the content is tailored to the specific patient and a face-to-face discussion takes place. With medudoc, patient education videos and IC Sheets are generated for each patient on the basis of the medical history, type of procedure and risk profile — generic content is the exception, not the standard.
This creates room for an additional benefit, particularly for airway questions: if the medical history indicates a possibly difficult airway (e.g. previous intubation problems or sleep apnoea), the video sent in advance can inform the patient at home — without time pressure — about anaesthetic techniques and possible alternatives such as regional anaesthesia. This is in line with the clinical recommendation of ÖGARI to actively inform patients about the advantages of regional anaesthesia when a difficult airway is suspected. The video does not replace the mandatory face-to-face consent discussion — it makes it more focused, because the basics are already known and more time remains for individual questions.
Where does medical responsibility lie in this workflow?
The final medical decision — including the airway assessment and the choice of anaesthetic technique — remains entirely with the physician. medudoc structures medical history data for the physician’s assessment and is not a medical device within the meaning of the MDR.
This applies regardless of the degree of digitalisation: even without a digital medical history, airway assessment on the day of the pre-anaesthesia visit is not a one-off step. The DGAI guideline requires the airway to be reassessed by the intubating person immediately before induction of anaesthesia — regardless of what was previously documented in the outpatient clinic or the admission interview. A structured digital medical history does not change this ultimate medical responsibility; it ensures that the treating physician goes into this assessment with better-prepared prior information.
