


Why does hardly anyone know the cost of a premedication visit?
Premedication – the physician’s preparation for an elective procedure through medical history, examination, patient information and risk classification – does not generate any revenue of its own in the reimbursement system. In the DRG system (Diagnosis Related Groups, the German case-based lump-sum system), it is priced into the case-based lump sum; the same principle applies in the Austrian LKF system (performance-oriented hospital financing). In the cost matrix of the InEK (Institute for the Hospital Remuneration System), the premedication visit disappears into the collective cost centre “Anaesthesia”. Without a revenue item of its own, there is no incentive to calculate it separately – which is why no reliable, current figure exists so far.
How long does a pre-anaesthesia consultation actually take?
Two recent prospective studies provide reliable time values – with a difference between 11 and 34 minutes that looks large at first glance but is easy to explain. The difference lies in the definition: do you measure only the discussion with the patient, or also the review of the findings they bring along?
| Study | Setting | Time measured |
|---|---|---|
| Kieninger et al. 2018, University Hospital Regensburg (prospective, 2,233 discussions over 38 working days) | Tertiary care hospital | Review of documents + discussion: 33.6 ± 16.3 min; mean patient waiting time 58.6 ± 30.3 min |
| Compère et al. 2022, four French hospitals (prospective, n = 1,007) | Mixed | Total consultation 11.2 ± 5.8 min (6.8 min information, 4.4 min clinical examination) |
The Regensburg group also measures the review of the documents patients bring along – and this is exactly what eats up time: the most frequent disruption in the process there was missing documents that, according to the internal standard, should already have been available. For a full cost calculation, the total physician time involved is relevant – discussion, review of findings, documentation and orders. The base case below assumes 25 minutes, with a range of 15 to 35 minutes.
What does a physician minute in the anaesthesia clinic cost?
Based on the 2024 collectively agreed pay rates (TV-Ärzte for university hospitals, TV-L, including the 25.59% employer social security contribution), a minute of an anaesthesia specialist’s time costs around €1.13. This recent calculation comes from Hierl, Schörner and Alt in Regensburg and covers only the personnel costs of the professional groups directly involved – without administration, cleaning, energy or material costs.
| Professional group | Personnel costs per minute |
|---|---|
| Anaesthesia specialist | €1.13 |
| Specialist anaesthesia nurse | €0.73 |
| Senior physician (surgical) | €1.39 |
| Resident physician (surgical) | €0.92 |
For registration and assistance in a clinic, around €0.50/min can additionally be assumed. According to the Federal Statistical Office, personnel costs accounted for just under 62% of total hospital costs in 2021 – the remaining share is accounted for by infrastructure, material costs and overheads.
How high are the full costs of a premedication visit?
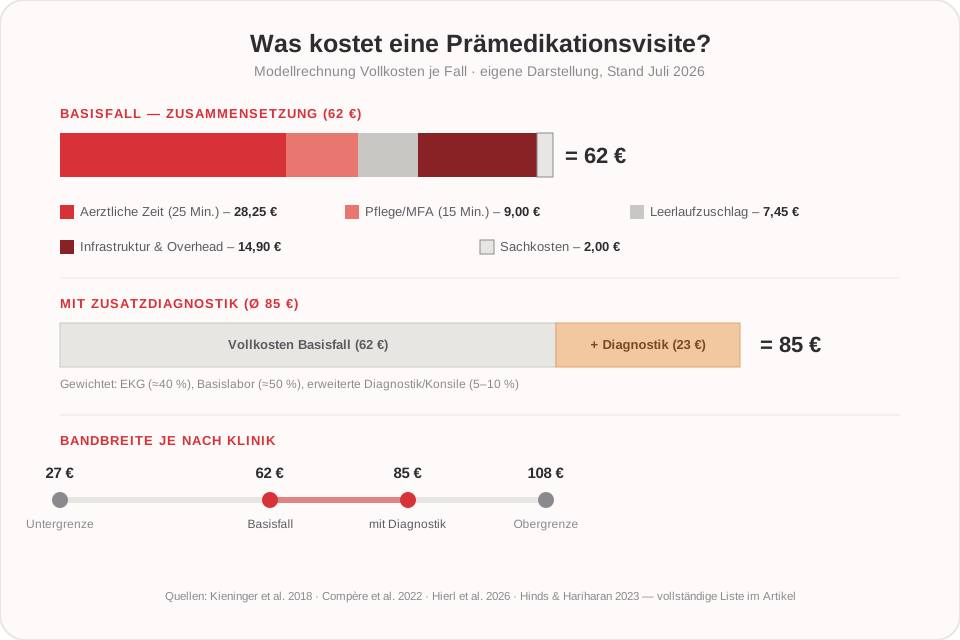
In the base case, the full costs are around €62 without additional diagnostics, with a range from €27 (lean process) to €108 (tertiary care hospital with high overheads). The following table shows the breakdown.
What is premedication?
Premedication is the preparatory medical measure before an elective procedure, carried out in particular by anaesthesiology. It comprises medical history, examination, patient information, risk classification and, where necessary, pharmacological preparation. In many hospitals, the pre-anaesthesia clinic is a separate workflow area within the preoperative process.
| Item | Assumption | Amount |
|---|---|---|
| Physician time | 25 min × €1.13/min | €28.25 |
| Nursing staff/medical assistant (registration, vital signs, file preparation, scheduling) | 15 min × €0.60/min | €9.00 |
| Direct personnel costs | €37.25 | |
| Idle time/standby surcharge (utilisation approx. 80%, no-shows, scheduling gaps) | +20% | €7.45 |
| Infrastructure and overheads (room, energy, cleaning, HIS/IT, administration, depreciation) | +40% on direct personnel costs | €14.90 |
| Direct material costs (consent sheet licence, printing, anaesthesia card) | €2.00 | |
| Total without additional diagnostics | ≈ €62 |
| Scenario | Constellation | Result |
|---|---|---|
| Lower bound | 15 min resident (≈ €0.95/min), 8 min medical assistant, lean process, 10% idle time, 30% overheads | ≈ €27 |
| Base case | see table above | ≈ €62 |
| Upper bound | 35 min specialist/senior physician (€1.25/min), 20 min nursing, 30% idle time, 50% overheads, tertiary care hospital | ≈ €108 |
What do additional diagnostics before the procedure cost?
If ECG (in approx. 40% of patients), basic laboratory tests (approx. 50%) and extended diagnostics or consultations (5–10%) are weighted realistically, an average of around €25 is added – the full costs including diagnostics are therefore about €85 (range €45–140). This is also where the biggest lever for control lies: not every patient needs an ECG or laboratory tests.
Hinds and Hariharan prospectively examined 636 elective patients and, based on the guideline of NICE (National Institute for Health and Care Excellence, the British health authority), classified 64% of all preoperative tests as not indicated; these non-indicated tests accounted for 59% of total diagnostic expenditure.
Does this estimate stand up to external comparison?
Summary: Yes – four independent checkpoints support the order of magnitude and suggest that the base case is, if anything, a conservative estimate.
- Direct comparison value: Lee and colleagues report a clinic cost rate equivalent to around 109 US dollars per patient for an anaesthesia clinic in Hong Kong – after conversion and taking into account the years that have passed since then, remarkably close to the estimate presented here.
- Updating the German value: In 2004, Bauer and colleagues put the premedication visit at €13.00 for 20 minutes of physician time. At today’s minute rate of €1.13, this corresponds to €22.60 – adding nursing, idle time and overheads brings you to the same order of magnitude as the base case.
- Cost structure around the clinic: In Lee et al., preoperative costs in the clinic group were lower, but total perioperative costs did not differ significantly – because postoperative bed costs accounted for around three quarters of total costs. Premedication itself is economically a small item.
- Patient perspective: In Toulouse, Ferre and colleagues compared teleconsultation with in-person attendance in 401 orthopaedic patients: mean saving of €122 per patient, with 22 instead of 130 minutes of time spent and no significant difference in postoperative complication rates.
What costs do patients themselves incur?
Summary: With an average waiting time of almost an hour plus travel there and back, two to three hours per visit are realistic – valued at €25 to €35/h plus travel costs, this results in €50 to €120 per case, which hospital calculations systematically leave out.
Together with the hospital’s full costs, this results in total societal costs of roughly €130 to €180 per consultation. A German preference study by Aust and colleagues shows that patients do value this time: of a fictitious budget of €100, €36 went towards the premedication visit being carried out by the same person who would administer the anaesthesia, and €26 towards waiting less than two hours.
Which four levers reduce the costs of premedication most effectively?
Summary: In descending order of impact: strict indication for additional diagnostics, complete documents when patients attend, appointment scheduling and utilisation, and telemedicine for low-risk patients.
- Strict indication for additional diagnostics. By far the largest single cost block is also the easiest to avoid – see the 64% figure from Hinds and Hariharan above.
- Complete documents when patients attend. The Regensburg data identify missing findings as the main disruptive factor in the process – every minute spent searching costs around €1.13.
- Appointment scheduling and utilisation. The idle-time surcharge is not an accounting trick but real standby costs. A more even flow of patients throughout the day directly reduces unit costs.
- Telemedicine for low-risk patients. From the hospital’s perspective, the saving is moderate; from a societal perspective – see the Toulouse data – it is considerable.
At their core, all four levers are questions of digitalising the preoperative workflow: they concern how complete the medical history data are before the appointment, how structured appointment planning is and for which patient groups an in-person appointment is necessary at all. medudoc’s digital preoperative workflow maps exactly these steps – from medical history and risk classification to patient education – in one continuous process. Via a FHIR interface, medical history data and previous findings are available in structured form before the appointment, which directly counteracts the cause of lost time described under lever 2. For patients in risk classes ASA I and ASA II (American Society of Anesthesiologists classification, grades I–II: healthy persons or persons with only mild systemic disease), who account for the majority of planned procedures, the consent discussion can also be conducted from home, depending on the hospital-specific configuration – the telemedicine approach described under lever 4. The decision on necessary additional diagnostics and every medical assessment remain entirely with the physician; medudoc structures and provides information for this assessment, but does not replace it.
The prospective study at University Hospital Würzburg shows how much structured processes and personalised video-assisted patient education can reduce the time needed for patient information. Where exactly time is lost in the intake process today is described in the article preoperative intake process: where physicians lose time.
What are the limits of this calculation?
Summary: This estimate is a model calculation, not a survey – three limitations are important for putting it into context.
- The overhead surcharge of 40% is the most uncertain assumption. It can only be derived from each hospital’s own cost centre accounting; a methodologically sound approach would be a time-driven activity-based costing survey with measured capacity cost rates.
- The personnel cost rates come from a German university hospital and, according to the authors, are expressly not generally applicable. Surcharges for on-call, night and weekend work are not included.
- The same logic applies to Austria, but the absolute pay rates differ. As the service is not separately scored in the LKF system either, the calculation there must also be done internally via cost centre accounting.
Note on the data basis: the calculation presented in this article is our own model calculation based on the cited literature values, as of July 2026. It does not replace a hospital-specific cost centre calculation. The assumptions on overheads, utilisation and the share of diagnostics are shown transparently and should be adapted to the respective site.
